

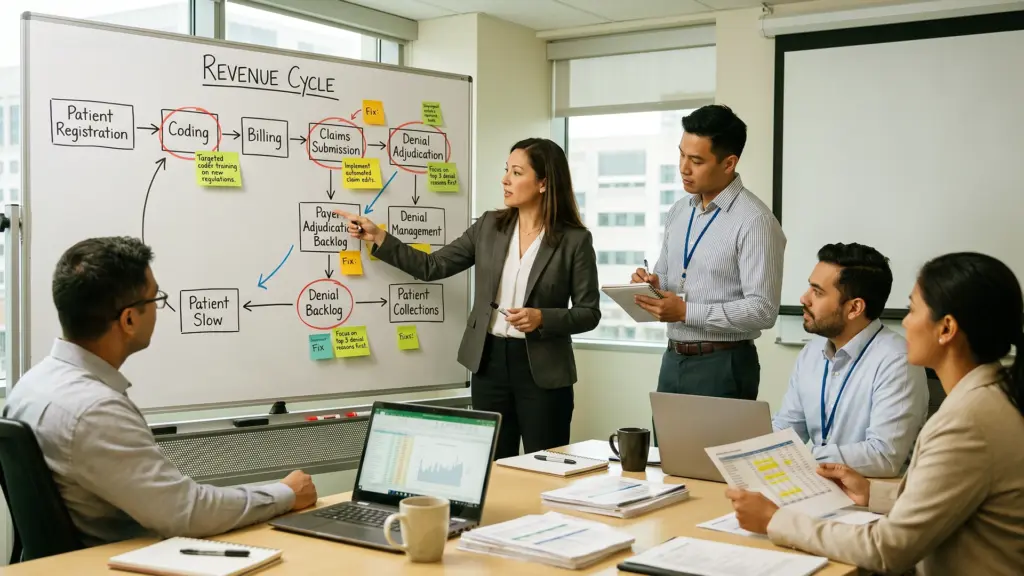
Most healthcare organisations don’t have one big revenue cycle problem — they’ve got a handful of smaller ones stacked on top of each other. A slow eligibility check here, a coding inconsistency there, a follow-up that never quite happens on schedule. None of it looks catastrophic in isolation, but together it adds up to slower payments and a financial picture that’s harder to trust than it should be.
That’s usually the moment organisations start looking into revenue cycle optimization services — not because everything’s broken, but because a handful of specific bottlenecks are quietly dragging down performance and nobody’s had the bandwidth to actually fix them properly.
Spotting the bottlenecks that actually matter
Not every inefficiency is worth chasing right away. The trick is figuring out which ones are actually costing real money versus which ones are just mildly annoying. A denial rate that’s crept up over the last two quarters is worth investigating. A slightly slower turnaround on one specific payer, less so — unless it’s happening across a huge share of your claims.
Look at where claims tend to stall. Is it before submission, sitting in a queue waiting for coding review? Is it after submission, with no consistent follow-up on anything that goes past 30 days? Or is it at reconciliation, where underpayments slip through because nobody’s cross-checking payments against contracted rates? Pinpointing the actual bottleneck matters a lot more than just assuming the whole process needs a rebuild.
Common bottlenecks and what usually causes them
A few patterns show up again and again across different organisations, regardless of size or speciality. Recognising which one matches your situation makes it a lot easier to know where to focus first:
- Claims stuck in coding review — usually a documentation or staffing capacity issue
- High first-pass denial rates — often tied to eligibility verification gaps
- Aging receivables past 90 days — typically a follow-up consistency problem
- Payment discrepancies going unnoticed — a reconciliation process that’s too manual
- Reporting delays — data scattered across systems that don’t talk to each other
Most organisations recognise at least two or three of these immediately. The good news is that fixing them individually tends to produce faster, more visible results than trying to redesign the entire revenue cycle from scratch.
Fixing eligibility and front-end gaps first
Front-end problems deserve attention before anything else, mainly because they cause the most downstream damage per error. A single incorrect eligibility check can turn into a denial, an appeal, and weeks of delay — all from one avoidable mistake at intake. Tightening up verification here has an outsized effect on everything that happens later.
This usually means making eligibility checks a non-negotiable step before any service gets scheduled, not something squeezed in when staff have a spare minute. It also means double-checking coverage details against what the patient actually reports, since assumptions here are where a lot of denials originate. Getting this stage right doesn’t eliminate every downstream problem, but it removes a meaningful chunk of them before they even start.
Tightening claim accuracy and reducing denials
Once front-end data is solid, the next lever is claim accuracy itself. Coding errors and incomplete documentation are still some of the most common denial triggers out there, and they’re largely preventable with better process discipline. Quality checks before submission — even quick ones — catch a surprising number of issues that would otherwise turn into a rejected claim weeks later.
Denial patterns are worth tracking closely too. If the same denial reason keeps showing up from the same payer, that’s a specific, fixable issue rather than random bad luck. Addressing the root cause, whether it’s a documentation gap or a misunderstanding of a particular payer’s requirements, tends to prevent a whole category of future denials rather than just resolving the ones already sitting in your queue.
Strengthening follow-up on outstanding claims
Aging receivables rarely happen because nobody cares — they happen because follow-up isn’t scheduled consistently enough to catch claims before they slip past the point of easy recovery. A claim that’s 30 days old is a lot easier to resolve than one that’s 120 days old, but without a structured follow-up cadence, claims tend to get attention only when someone happens to notice them.
Setting clear timelines for follow-up — checking status at 15 days, escalating at 30, appealing denials promptly rather than letting them sit — makes a measurable difference over time. It’s not complicated work, but it does require consistency, which is exactly the kind of thing that falls apart when staff are already stretched thin handling new claims coming in.
When it makes sense to bring in outside expertise
Sometimes the bottleneck isn’t really a process problem — it’s a bandwidth problem. If your team already knows what needs fixing but simply doesn’t have the hours to execute consistently, that’s usually the point where bringing in outside support starts to make sense. It’s not an admission that something’s wrong internally; it’s just recognizing that some tasks need dedicated attention your current team can’t reliably give them.
This is especially true for repetitive, high-volume work like eligibility checks or A/R follow-up, where consistency matters more than specialized judgment. Bringing intrusted billing experts to handle these specific bottlenecks can free your internal staff to focus on the more complex account issues that actually need their attention and expertise.
Measuring whether the fixes are actually working
None of this is worth doing if you’re not tracking whether it’s making a difference. Denial rate should be trending down within a few months if front-end and coding fixes are working. Days in A/R should shrink if follow-up consistency has improved. Clean claim rate is a good early indicator too, since it reflects whether accuracy improvements are actually holding up under real volume.
Check these numbers on a regular schedule rather than waiting for an annual review to notice a problem. Small, consistent improvements across these metrics usually mean the specific bottlenecks you targeted are actually resolving, rather than just feeling better in the moment without real measurable change.
Keeping the revenue cycle from drifting back into old patterns
Fixing bottlenecks once doesn’t mean they stay fixed forever. Staff turnover, new payer requirements, or just gradual process drift can bring the same problems back within a year if nobody’s watching. Building in regular reviews — checking denial trends, A/R aging, and claim accuracy on a recurring basis — is what actually keeps improvements from quietly unraveling. It’s a lot easier to catch a problem early than to rediscover it six months later as a bigger issue than it needed to be.